
Knee Ligament Reconstruction
PCL Reconstruction Surgery in Ludhiana, Punjab
The posterior cruciate ligament (PCL) is one of the strongest ligaments of the knee and is commonly injured during road traffic accidents, sports injuries, and high-impact trauma. Unlike ACL injuries, many isolated PCL tears can be successfully treated without surgery. However, patients with persistent instability, combined ligament injuries, or high-demand athletic requirements may benefit from arthroscopic PCL reconstruction.
At Eva Hospital, treatment is individualised after clinical examination, MRI evaluation and assessment of associated ligament and meniscal injuries.

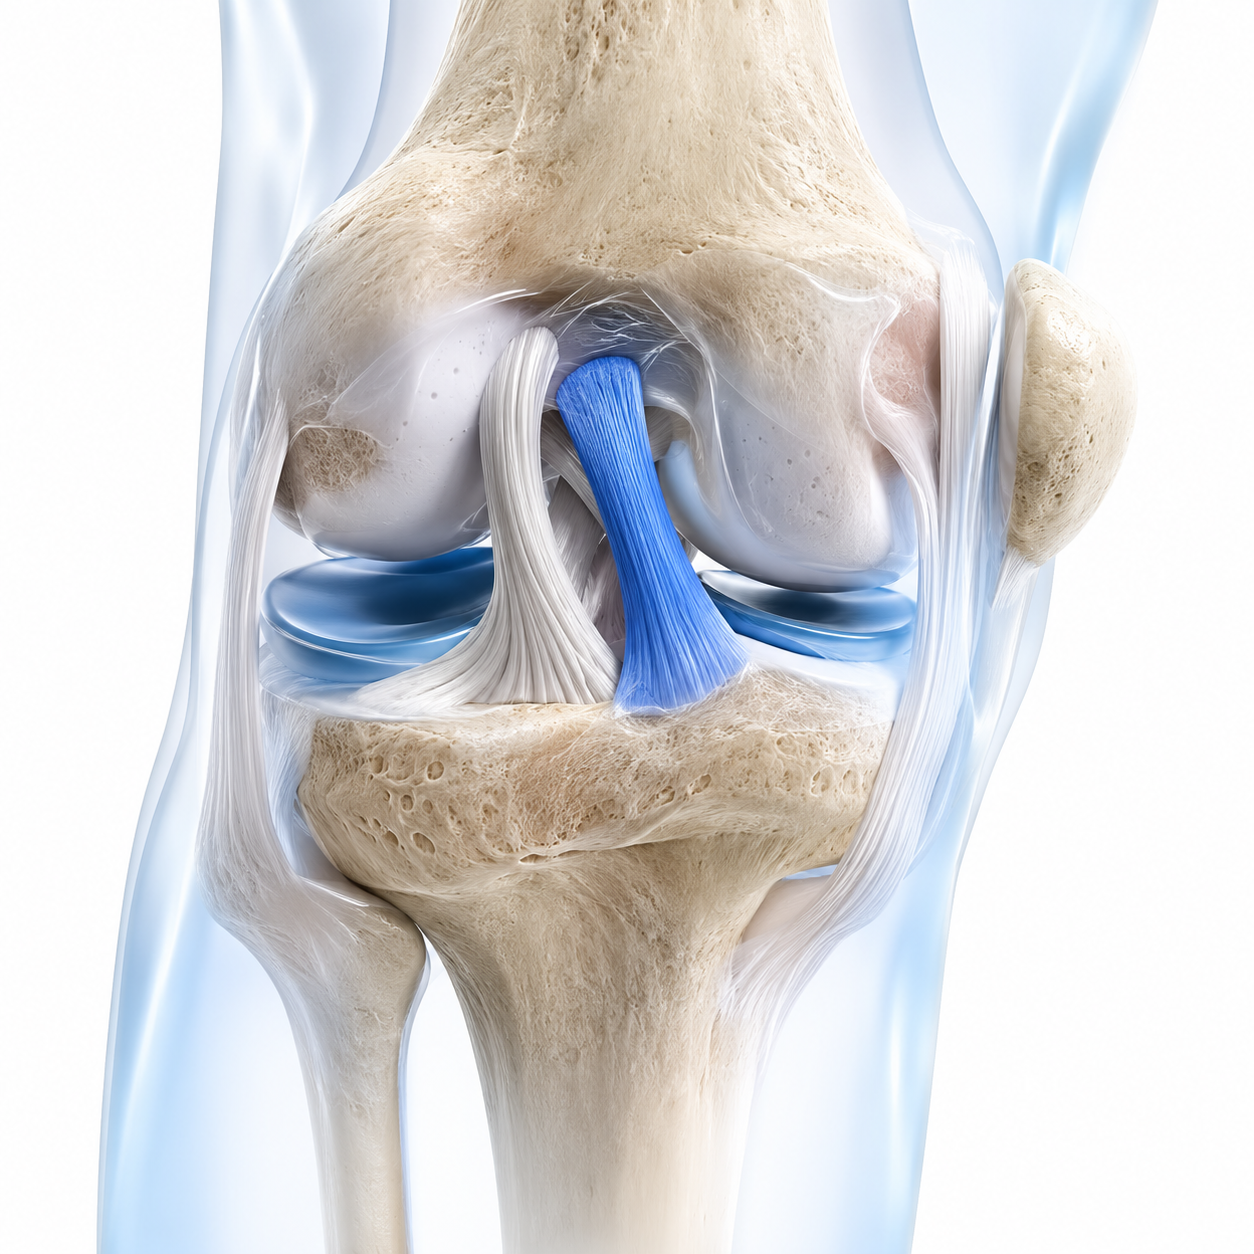
Understanding the injury
What is the Posterior Cruciate Ligament?
- Provides the main restraint against backward (posterior) movement of the tibia
- Contributes to overall rotational stability of the knee alongside the ACL
- Works with the posterolateral corner structures to control complex movements
Disclaimer: Images are AI-generated for illustrative purposes only.
How Does a PCL Tear Occur?
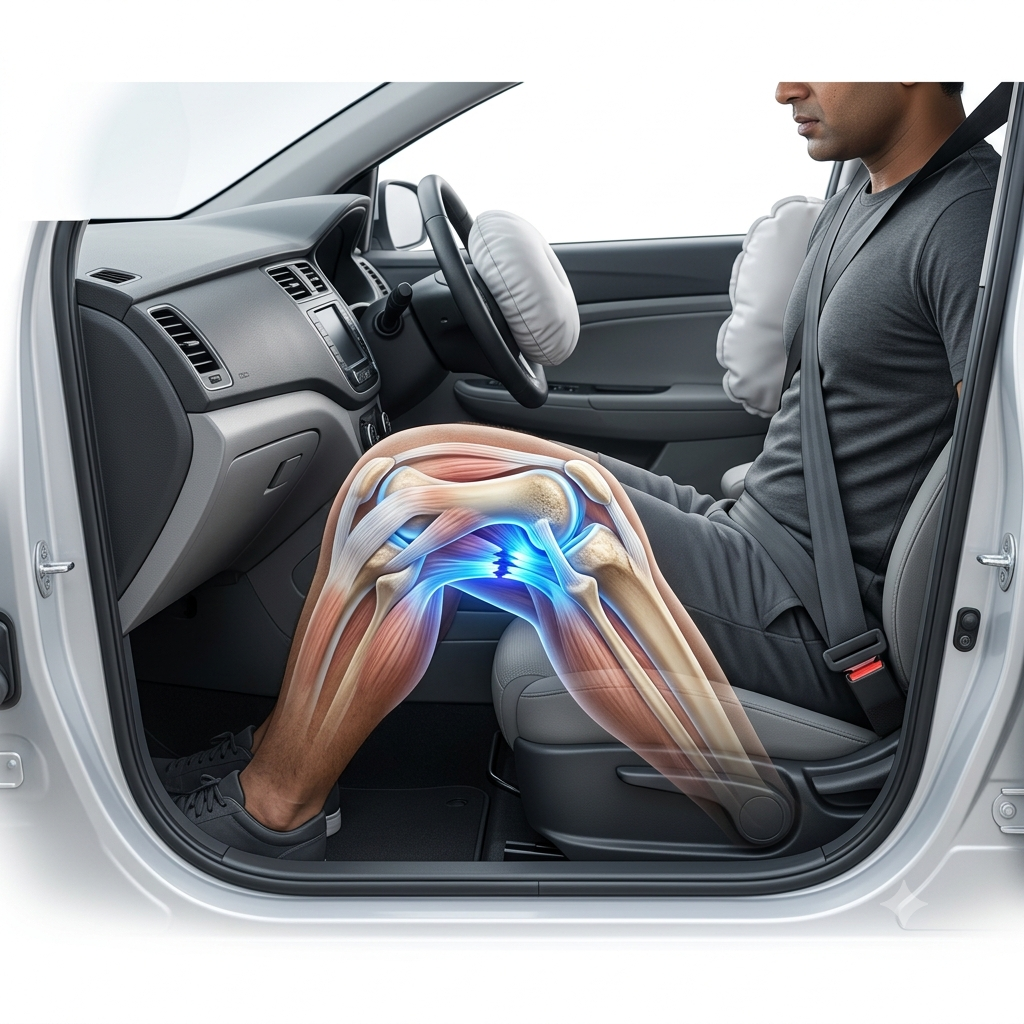
Dashboard Injury

Road Traffic Accidents

Sports Injuries

Hyperflexion Injuries

Hyperextension Injuries
Symptoms of a PCL Tear

Posterior Knee Pain
Swelling

Instability

Difficulty Descending Stairs
Knee "Slipping Backwards"

Reduced Sporting Performance
Disclaimer: Images are AI-generated for illustrative purposes only.
How is a PCL Tear Diagnosed?
History
Clinical Examination
Posterior Drawer Test
Posterior Sag Sign
Quadriceps Active Test
MRI
Standing X-rays
Stress Radiographs (Selected Patients)
Partial vs Complete PCL Tear
Grade I
Grade II
Grade III
Can a PCL Tear Heal Without Surgery?
Conservative Treatment Often Works
- Grade I injuries
- Grade II injuries
- Selected Grade III injuries in lower-demand patients
- Bracing to support the knee during early healing
- Structured physiotherapy and quadriceps strengthening
When Surgery Becomes Appropriate
- Persistent instability despite adequate rehabilitation
- Combined ligament injury (e.g. ACL, PLC involvement)
- A displaced avulsion fracture
- High-level athletic demands
- Failed conservative treatment
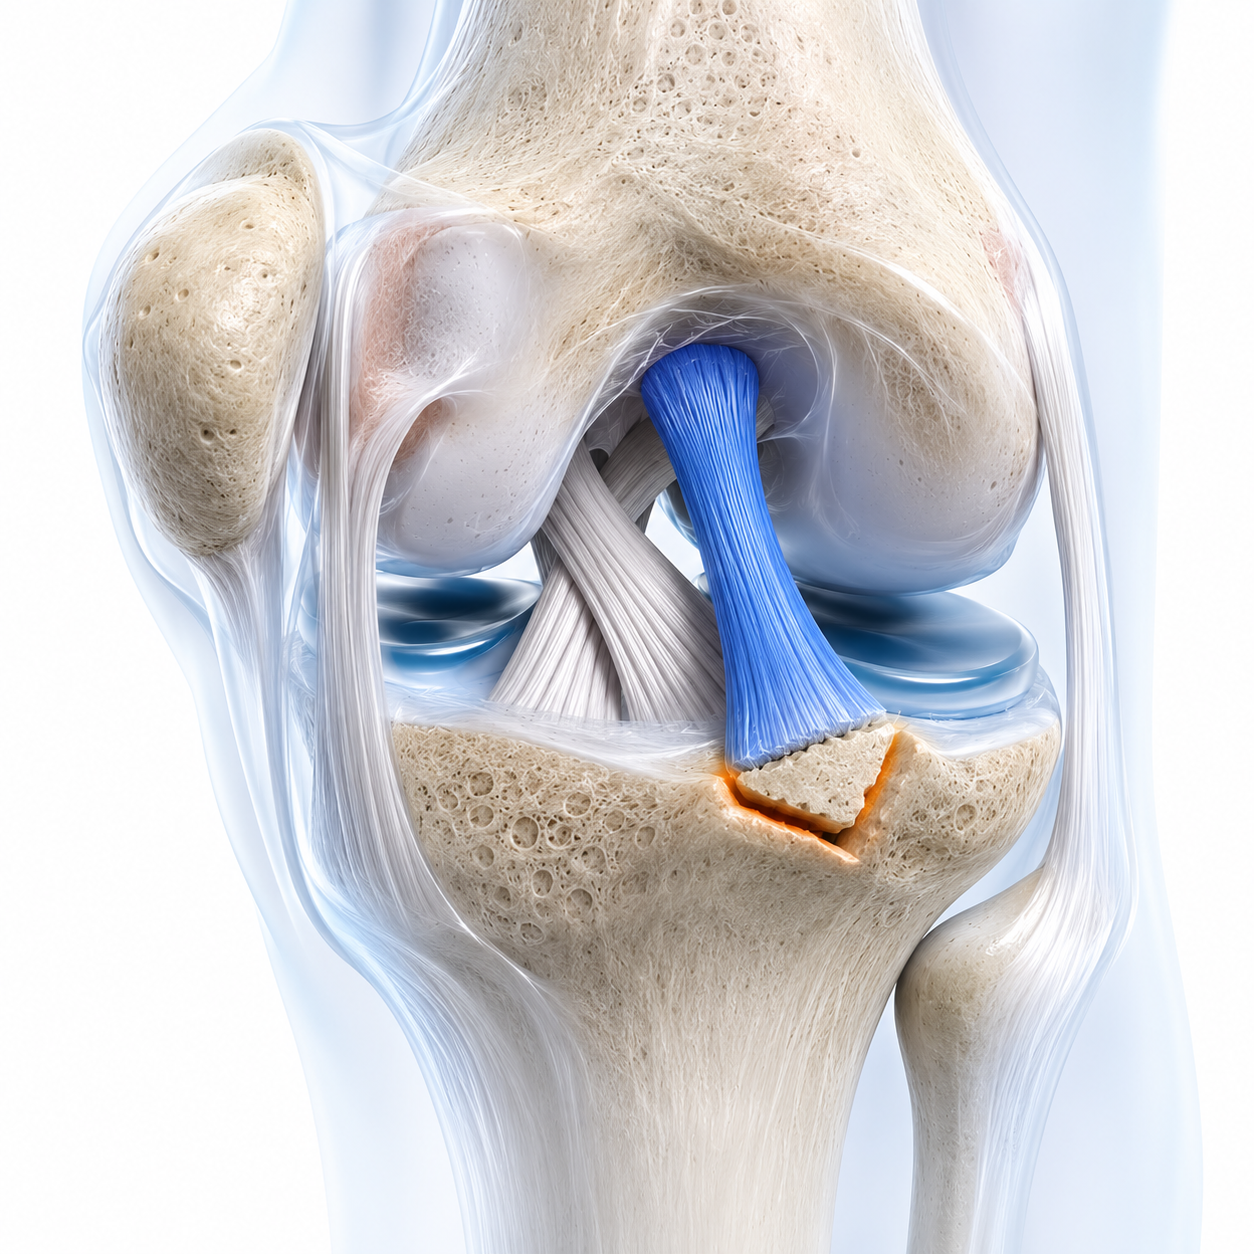
PCL Avulsion Injuries
- Femoral avulsion — the fragment separates from the thigh bone attachment
- Tibial avulsion — the fragment separates from the shin bone attachment, often seen after dashboard injuries
Disclaimer: Images are AI-generated for illustrative purposes only.
Combined Ligament Injuries
ACL + PCL Injury
PCL + PLC Injury
Knee Dislocation
Multiple Ligament Injuries
Risks of Persistent Instability
Persistent Instability
Meniscus Damage
Cartilage Injury
Early Arthritis
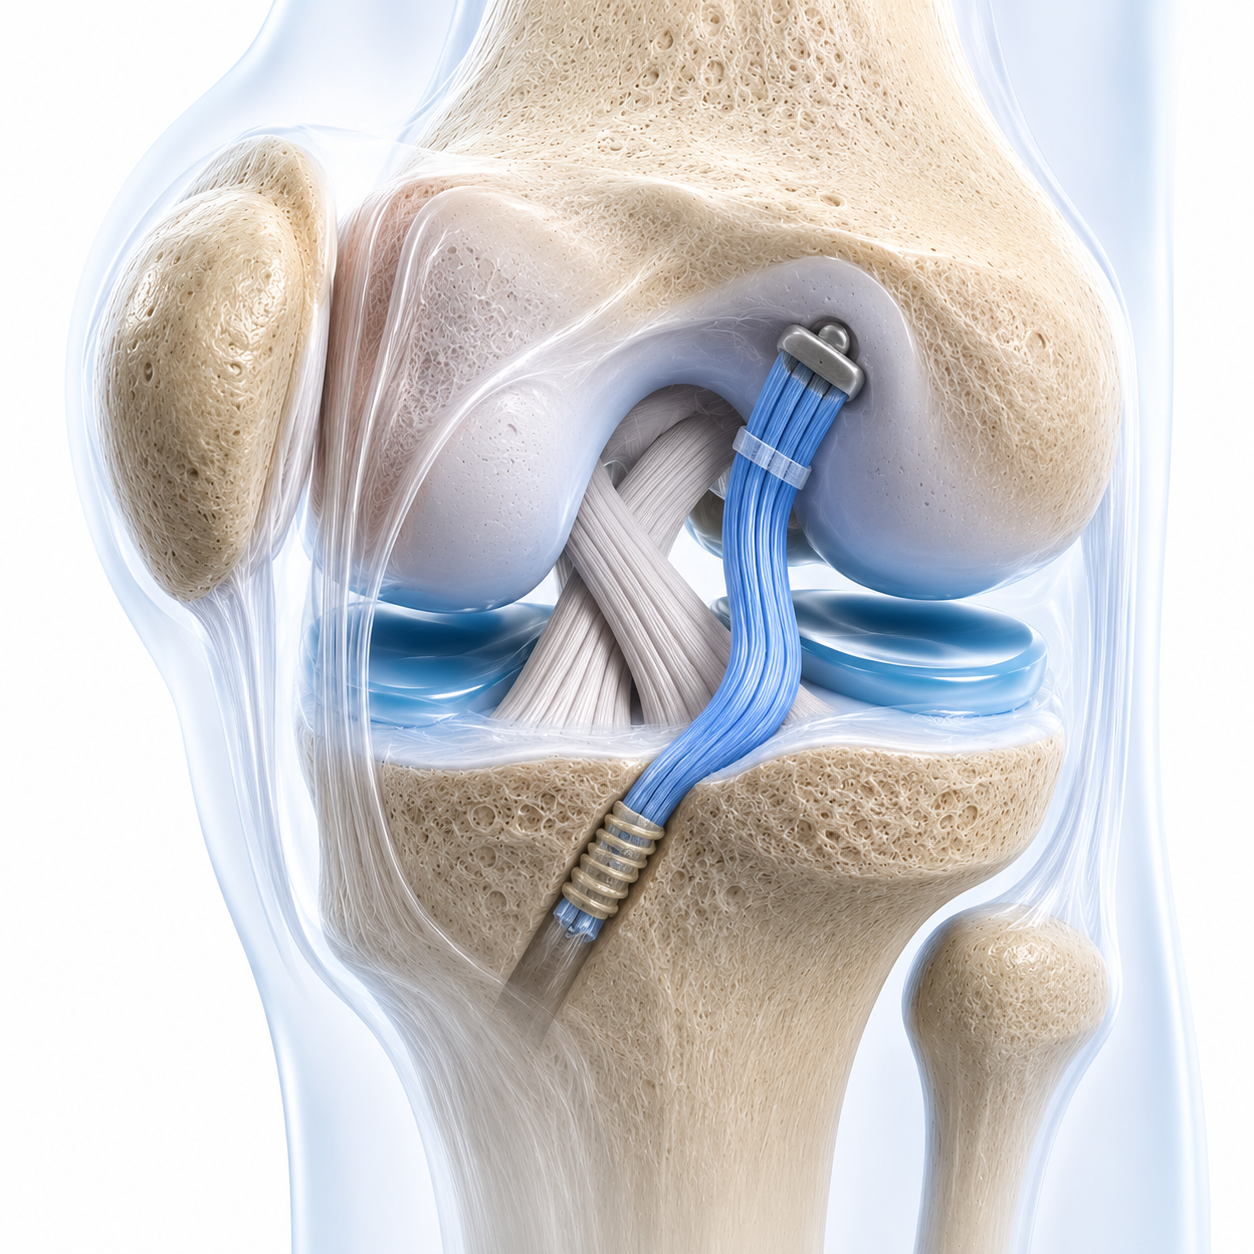
PCL Graft Options
| Graft Type | Advantages | Considerations |
|---|---|---|
| Hamstring Tendon | Adequate strength for many PCL reconstructions, reliable harvest technique, and commonly used. | May require doubling or combining tendon strands to achieve the desired graft thickness and strength. |
| Quadriceps Tendon | Provides a larger and thicker graft, making it well suited for the higher mechanical demands of PCL reconstruction. | Harvest technique is more demanding, and temporary donor-site discomfort may occur. |
| Allograft (Donor Tissue) | No donor-site morbidity, shorter operative time, and particularly useful for complex or multi-ligament knee reconstructions. | Often preferred for older or lower-demand patients because graft incorporation can be slower than autografts. |
PCL Fixation Methods
Disclaimer: Images are AI-generated for illustrative purposes only.
Arthroscopic PCL Reconstruction, Explained Simply

Arthroscopic Assessment

Graft Harvest & Preparation

Tunnel Creation

Graft Passage

Graft Fixation

Associated Repairs
Internal Bracing in PCL Reconstruction
Rehabilitation After PCL Reconstruction
| Rehabilitation Phase | What to Expect |
|---|---|
| Weeks 0–2 | Bracing in full extension, protected weight-bearing, and avoiding positions that place excessive stress on the healing PCL graft. |
| Weeks 2–6 | Gradual, controlled range-of-motion exercises with continued brace support and progressive quadriceps strengthening. |
| Weeks 6–12 | Progressive strengthening, balance training, and gait normalisation as brace use is gradually reduced. |
| 3 Months | Advanced strengthening exercises with the introduction of controlled functional movement patterns. |
| 6 Months | Sport-specific drills begin under professional supervision based on strength, stability, and functional progress. |
| 9 Months | Functional assessment determines readiness for higher-demand sports, with return-to-play timing individualised for each patient. |
Return to Sports After PCL Reconstruction

Drive

Cycling

Gym

Running

Pray (Floor-Sitting)

Kabaddi

Football
Disclaimer: Images are AI-generated for illustrative purposes only.
Risks and Expectations
It is important to understand the possible risks of PCL reconstruction.
- Infection
- Residual laxity
- Stiffness
- Neurovascular injury
- Re-tear
- Deep vein thrombosis (DVT)
Our Approach to PCL Reconstruction
Individualised Treatment Planning
Non-Operative Options
Arthroscopic Surgery
Combined Ligament Injuries
Structured Rehabilitation
Return-to-Sport Assessment
ACL vs PCL Injury – What's the Difference?
| Feature | ACL Injury | PCL Injury |
|---|---|---|
| Primary Function | Prevents the shin bone from sliding forward and provides rotational stability during pivoting movements. | Prevents the shin bone from moving backward and helps stabilise the knee during bending and weight-bearing. |
| Common Causes | Sudden twisting, pivoting, rapid deceleration, or awkward landing during sports. | Direct impact to the front of a bent knee, motor vehicle dashboard injuries, or falls onto a flexed knee. |
| Symptoms | Sudden pop, immediate swelling, knee instability, and difficulty changing direction. | Pain at the back of the knee, swelling, feeling of the knee moving backward, and discomfort while walking downhill or descending stairs. |
| Diagnosis | Clinical examination with Lachman and Pivot Shift tests, supported by MRI when required. | Clinical examination using the Posterior Drawer and Posterior Sag tests, confirmed with MRI if needed. |
| Treatment Approach | Physiotherapy for selected cases; reconstruction commonly advised for active individuals with complete tears. | Many isolated injuries respond well to rehabilitation, while surgery is reserved for severe instability, avulsion fractures, or combined ligament injuries. |
| Recovery Outlook | Return to unrestricted sports commonly takes 9–12 months following reconstruction and rehabilitation. | Recovery depends on injury severity and treatment method, with rehabilitation tailored to individual functional goals. |
Related Pages
Return to Sports After Ligament
Frequently Asked Questions
The ACL controls forward movement of the shin bone and is usually injured through twisting or pivoting, while the PCL controls backward movement and is more often injured by a direct blow to a bent knee, such as in a road traffic accident.
Yes — many isolated PCL tears, especially Grade I and II injuries, heal well with bracing and structured physiotherapy. Surgery is reserved for persistent instability, combined ligament injury, displaced avulsion, or high athletic demand.
It is the classic mechanism of PCL injury, where a bent knee strikes the dashboard during a car collision, forcing the shin bone backward and straining or tearing the PCL.
There is no universally ‘best’ graft. Hamstring, quadriceps tendon and allograft each have advantages; the right choice depends on your age, activity level and whether other ligaments are involved.
Most patients can consider driving around 4–6 weeks after surgery, once knee control and comfort allow safe braking and steering.
Many athletes return to football, typically after around nine months or more, once functional and strength testing confirm readiness.
Ongoing instability and associated meniscus or cartilage damage are risk factors for early arthritis, which is one reason appropriate treatment and rehabilitation matter.
Rehabilitation is typically a longer, more protected process than ACL rehab, often extending to 9 months or more before high-demand sport is resumed.
No. Many isolated PCL injuries are successfully managed without surgery. Surgery becomes appropriate for specific situations such as persistent instability or combined ligament injury.
It is a complete tear with marked posterior instability, often associated with injury to other knee ligaments, and more likely to require surgical treatment.
Yes. Combined ACL and PCL injuries usually cause significant instability and typically require surgical reconstruction of both ligaments.
The PLC is a group of structures on the outer back part of the knee that often works alongside the PCL for stability; combined PCL and PLC injuries need careful, coordinated treatment planning.
Through a combination of patient history, clinical tests (posterior drawer, posterior sag sign, quadriceps active test), and MRI to confirm the tear and check for associated injuries.
It refers to the shin bone gradually settling backward under gravity — a specific concern that shapes early PCL rehab protocols, including bracing in extension to protect the healing graft.
In some patients, an untreated PCL tear can contribute to ongoing instability and increase the risk of secondary meniscus or cartilage damage over time, though many isolated tears remain stable long-term with good muscle strength.
The posterior drawer test, posterior sag sign, and quadriceps active test are the main clinical tests, usually supported by MRI confirmation.
Most patients are admitted for a short stay, as bracing, early rehabilitation planning and pain management are set up before discharge.
Knee Injury Involving the PCL?
Consult the Orthopaedics Department at Eva Hospital, Pakhowal Road, Ludhiana.